
Writings
DON’T DIE OF INJECTING PEPTIDES!
Originally published on Substack.
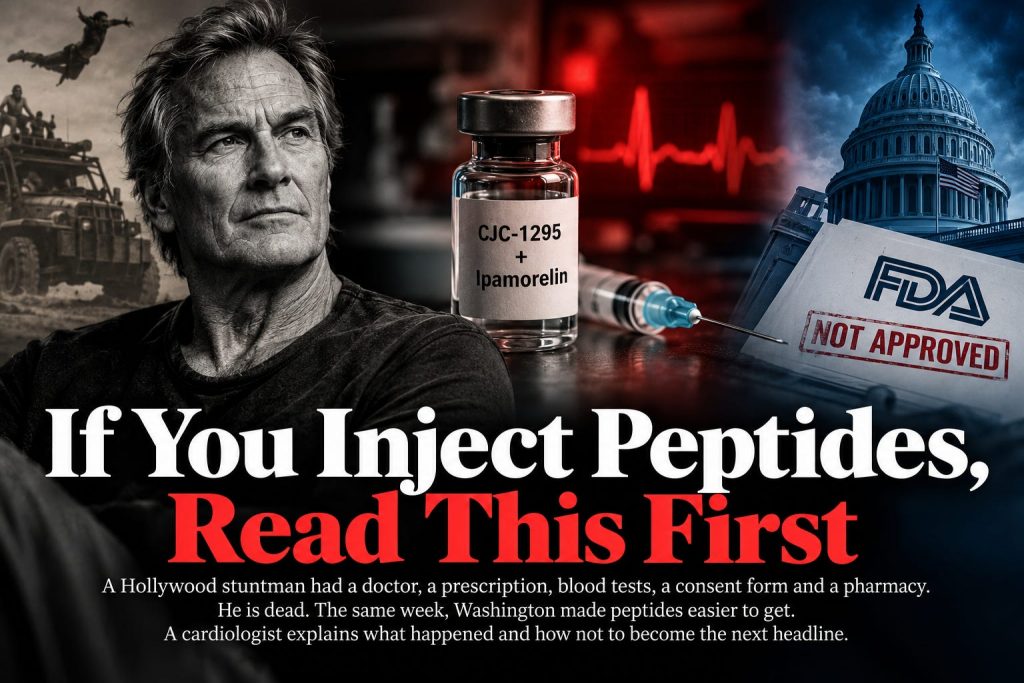
Richard Norton spent fifty years taking hits for a living.
He fought Chuck Norris on screen. He trained Scarlett Johansson, Margot Robbie and Tom Hardy. He guarded David Bowie. He played the Prime Imperator in Mad Max: Fury Road. If anyone had earned the right to feel indestructible at 75, it was him.
He died from a small injection he gave himself at home.
On Wednesday, a coroner in Victoria, Australia, ruled on what killed him. Coroner David Ryan found that Norton died after injecting two peptides, CJC-1295 and ipamorelin, and that he had been using more than his doctor prescribed. The injection set off an anaphylactic reaction, and the anaphylaxis caused cardiac arrest. geomensjournal
It is believed to be the first confirmed death in Australia from unapproved peptide use. abc
I have practiced cardiology for nearly thirty years. I have run codes on people whose hearts stopped from a bee sting, a dye injection or a single antibiotic dose. Norton’s death did not surprise me. The details of it should frighten you, because he did almost everything “right.”
He did everything the wellness industry tells you to do
This was not a man buying powder from a website. Look at the safeguards he had:
-
A physician. Norton was interested in peptide therapy and went to a medical practitioner, Dr. Jerzy Muchnicki. abc
-
Testing. He got the peptides only after blood tests and a CT scan. mensjournal
-
Informed consent. On March 19, 2025, he was prescribed CJC-1295 and ipamorelin after signing a consent form that listed anaphylaxis among the risks. aroundprague
-
Disclosure. His doctor explained that the therapy was experimental, described its risks, and told him the substances were not approved by Australia’s drug regulator for that use. ibtimes
-
A pharmacy. The peptides came from an interstate compounding pharmacy. miragenews
Then came the part every clinic hears and few take seriously. In the days before he died, Norton told his doctor he felt good and the peptides were helping. He later told a clinic nurse he had been giving himself double the prescribed dose, and she told him to go back to the prescribed dose starting the following week. abcozarab
He never got to the following week. He died at the Alfred Hospital on March 30, 2025. aroundprague
Feeling good is not a safety signal. It is the most dangerous moment in any self-experiment, because that is when people decide that if some is good, more is better.
What anaphylaxis does to the heart
People think of anaphylaxis as an allergy problem: hives, a swollen lip, an EpiPen. To a cardiologist, it is a circulatory collapse.
When the immune system goes into anaphylaxis, blood vessels throughout the body dilate at once. Fluid leaks out of the circulation into the tissues. Blood pressure falls, sometimes within minutes. The heart pumps harder to compensate, but the coronary arteries, which fill during the heart’s resting phase, are starved of pressure. The heart muscle itself stops getting enough oxygen. Rhythm becomes unstable. Then it stops.
That is the sequence the autopsy describes. The forensic pathologist found that the cardiac arrest caused oxygen-starvation injury to the brain, the bowel and the heart muscle. parade
Notice the first warning sign in the reports: he felt hot and flushed. Flushing is listed as a “common, mild” side effect of these peptides on almost every clinic website. In the wrong person, on the wrong day, at the wrong dose, it is the first minute of anaphylaxis.
Three factors make anaphylaxis more deadly, and they are common in the exact population buying “anti-aging” injections:
-
Age. Older hearts and arteries tolerate a sudden pressure drop poorly.
-
Asthma. Norton had asthma, osteoarthritis and two prior shoulder reconstructions. Asthma is one of the strongest predictors of fatal anaphylaxis. ozarab
-
Beta-blockers. Millions of people over 60 take them for blood pressure or rhythm. They can make anaphylaxis more severe and blunt the response to epinephrine, the one drug that reverses it.
No one selling you a peptide “stack” is screening for these factors the way a cardiologist would.
Meanwhile, in Washington
On the same day the coroner released his findings, the United States moved in the opposite direction.
HHS said it will not take enforcement action against state-licensed pharmacies, federal facilities or licensed physicians that compound BPC-157 and five other unapproved peptides while FDA works on rulemaking. The other five are epitalon, KPV, MOTS-c, Semax and TB-500. ajmc
Here is what the headlines are skipping:
This is not an approval. HHS frames it as enforcement discretion. None of the six peptides is FDA-approved, and because compounded drugs are not FDA-approved, FDA does not review their safety, effectiveness or quality before they reach patients. ajmc
FDA’s own scientists said no. An FDA advisory committee voted 8-6, with one abstention, to recommend BPC-157, KPV and TB-500 for compounding, and ultimately backed six of the seven peptides it reviewed, overruling career FDA scientists who had recommended against all seven. ajmc
There are real guardrails, and you should demand them. Compounders must source from FDA-registered manufacturers with a certificate of analysis showing identity, purity, potency and the absence of contaminants such as endotoxins and heavy metals, must report serious adverse events to MedWatch, must make single-ingredient products only, and need a patient-specific prescription. ajmc
The single-ingredient rule matters. A BPC-157 and TB-500 combination falls outside the policy even though each peptide is covered on its own. Every “stack” sold as a convenience is now, by HHS’s own definition, outside the safe harbor. drugtopics
The peptides that killed Norton are not even on the list. CJC-1295 and ipamorelin are not among the six. Clinics in the US already prescribe them. The new policy will make many people feel that “peptides are legal now,” and that feeling will spill over onto compounds no one has reviewed at all.
To be fair to HHS, the policy has a real public-health argument behind it. Until now, people could order BPC-157 or TB-500 from unregulated websites without seeing a doctor; under the interim policy they would need a prescription and a licensed compounding pharmacy. The gray market is genuinely dangerous: one obesity medicine specialist reported that gray-market peptides often contain only 5% to 75% of the labeled amount, and some contain arsenic at up to 10 times acceptable levels. CNNajmc
A cleaner product is better than a dirty one. But a clean vial of an unproven drug is still an unproven drug. Norton’s was dispensed by a pharmacy.
The BPC-157 evidence, honestly
BPC-157 is called the “Wolverine peptide.” It is sold for tendons, guts, joints and recovery. Here is the entire human evidence base.
A systematic review published October 8, 2026 in Acta Orthopaedica Belgica searched Embase, PubMed, the Cochrane Library and ClinicalTrials.gov through June 1, 2026, and found just three human studies covering 30 people total. draxe
Those 30 people break down as 16 with knee pain, 12 with interstitial cystitis, and 2 in a safety study. None was a randomized controlled trial. draxewe-heart
Thirty people. No placebo group. No randomization. For comparison, a new blood pressure pill typically has to be tested in thousands.
The animal data are extensive and genuinely interesting. A 2025 systematic review in the American Journal of Sports Medicine screened 544 articles on BPC-157 for orthopedic uses; of the 36 studies that qualified, 35 were in animals. Rats are not small people. Most drugs that heal rats never help humans. topdoctormagazine
Use is surging anyway. In one clinical-notes database, newly confirmed BPC-157 users rose roughly 33-fold, from 4 in early 2020 to 134 in early 2026. And the safety reports are starting to appear: FDA’s adverse event system has logged 10 serious reports tied to BPC-157 since 2021, 8 of them in 2026, though these reports do not prove causation. ajmcajmc
That is what a rising signal looks like in the early innings.
I am not anti-peptide
Insulin is a peptide. Semaglutide is a peptide. Some of the most important drugs I prescribe are peptides, and they have saved more lives than any supplement ever will.
The difference is not the molecule. It is the evidence. Semaglutide earned its place through trials in tens of thousands of people, with hard outcomes like heart attacks and deaths counted. BPC-157 has 30 people and a lot of Instagram.
When someone tells you a peptide is “natural” because your body makes similar molecules, remember: your body also makes adrenaline. Dose, route and timing are the whole story.
If you are going to inject a peptide anyway, do these 9 things
I would rather you be safe than right. If you have made your decision, protect yourself:
-
Ask what it was tested in. Humans or rats? How many people? For how long? Was there a placebo group? If the answer is “it’s been used for years,” that is not a study.
-
Never exceed the prescribed dose. Not double. Not “a little extra on recovery days.” Dose is not a volume knob.
-
Take the first dose under observation, ideally in a medical office, and wait at least 30 minutes.
-
Never inject alone. Make sure someone nearby knows what you took.
-
Know the warning signs: flushing, itching, hives, throat or chest tightness, wheezing, lightheadedness, a racing heart. Treat them as an emergency. Call 911.
-
Ask your doctor about an epinephrine auto-injector, especially if you have asthma, prior allergic reactions or heart disease.
-
Tell your prescriber everything: asthma, allergies, beta-blockers, heart history, every other peptide and supplement you use.
-
One compound at a time. If you stack three and react, no one can tell which one did it. Demand a certificate of analysis, and never use anything labeled “research use only.”
-
Report reactions to FDA’s MedWatch. Every report helps the next person.
And if you are on the growth hormone axis, as with CJC-1295 and ipamorelin, ask your doctor to monitor your IGF-1 and blood sugar. Long-term growth-signal stimulation has unanswered questions around cancer and metabolism that no one has studied adequately.
Why I wrote Longevity Unmasked
Every week, patients bring me their screenshots. A podcast clip about peptides. A clinic menu with eleven injectables. A $400-a-month “longevity protocol” with no data behind it.
They are not foolish. They are drowning. The longevity world has more confident voices than ever and less honesty about the evidence. The people selling the hope are rarely the ones in the emergency room when it goes wrong.
So I sat down and wrote the book I wish I could hand to every one of them.
Longevity Unmasked: A Cardiologist Reveals What Works, What’s Hype, and How to Live (Almost) Forever answers 433 of the questions my patients actually ask, about peptides, supplements, hormones, fasting, scans, wearables, cold plunges and everything else. Every answer is graded by the strength of its evidence, so you can see at a glance what is proven, what is promising, and what is marketing wearing a lab coat.
It is not a book that tells you to do nothing. It is a book that tells you where your time, money and risk are actually buying you years.
📘 Get the book: Longevity Unmasked on Amazon
🌐 Explore the answers: LongevityUnmasked.com, the companion site, where you can search the book’s questions and find evidence updates as new studies come out. Peptide research is moving fast, and the site moves with it.
One last thought
Richard Norton made his living out of controlled risk. Every stunt was rehearsed, measured and backed by a crew ready to catch him.
The injection had no rehearsal and no crew. It had a vial, a syringe, and the very human belief that if something is making you feel young again, more of it will make you feel younger.
The search for more life is noble. It is one of the oldest longings we have. But wisdom has always been knowing the difference between what promises life and what actually gives it.
Ask what it was tested in. Respect the dose. Never inject alone.
Live longer. Live wiser.
— Dr. Afshine Emrani, MD, FACC
This article is for education and is not personal medical advice. Talk with your own physician before starting or stopping any therapy.





